I remember sitting in a humid warehouse outside Goma, staring at a stack of glossy brochures that detailed the complex biochemical markers of protein deficiency. The pamphlets were beautiful, filled with colorful charts explaining how malnutrition is diagnosed and treated through high-level clinical assessments. But as I looked at the empty landing strip and the broken axle on our primary transport truck, I realized those charts meant nothing if we couldn’t get the Ready-to-Use Therapeutic Food (RUTF) past the checkpoint. In the field, we don’t have the luxury of debating nuanced metabolic indicators; we have the reality of whether a child’s mid-upper arm circumference is below the threshold and if the supply chain can actually deliver the recovery formula before it’s too late.
I am not here to give you a lecture on medical theory or the latest academic white papers. Instead, I’m going to strip away the jargon and tell you how this actually works when the electricity is out and the roads are washed away. I will walk you through the practicalities of how malnutrition is diagnosed and treated using the tools that actually survive a bumpy ride in the back of a Land Cruiser. We will focus on the metrics that matter: the accuracy of the MUAC tapes and the logistical reality of keeping a patient stable until the next shipment arrives.
Table of Contents
Decoding the Signs of Severe Acute Malnutrition

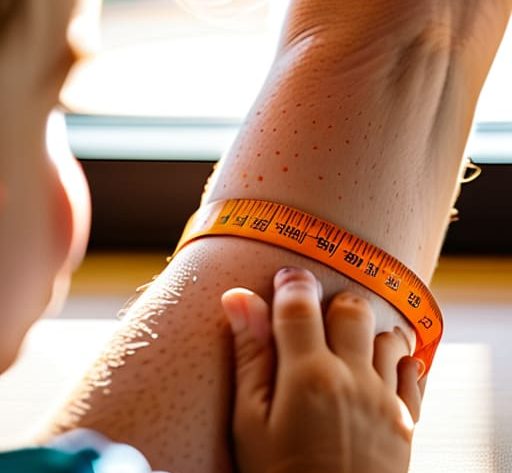
When I was working in the field, I learned quickly that a child’s appearance can be deceptive. You can have a kid who looks relatively “normal” but is internally starving, or one who is swollen with edema and looks “healthy” to the untrained eye. We don’t rely on gut feelings or pity; we rely on mid-upper arm circumference measurement. I’ve spent more hours than I care to admit staring at a MUAC tape, watching that colored strip move from green into the red zone. That red strip is the only metric that matters. It’s the line between a manageable case and a logistical emergency.
Identifying the signs of severe acute malnutrition isn’t just about looking for ribs. It’s about checking for bilateral pitting edema—that tells you the body is losing its ability to hold fluid—and assessing for wasting. We use specific nutritional assessment methods to differentiate between simple hunger and the kind of metabolic collapse that requires immediate stabilization. If the child has lost the subcutaneous fat under the skin, the window for intervention is closing. It isn’t a medical debate for us; it’s a race against a clock that most people don’t realize is even running.
Nutritional Assessment Methods Beyond the Surface

In the field, we don’t have the luxury of waiting for blood panels or high-tech lab results. When you are standing in a dusty clinic in South Sudan or eastern DRC, you rely on what you can measure with your hands and a piece of colored tape. The most reliable tool in my kit was always the MUAC tape. This mid-upper arm circumference measurement is the frontline reality; it’s a blunt, fast, and brutally effective way to separate a child who is merely underweight from one who is sliding into a life-threatening crisis. If the tape hits the red zone, the conversation shifts from “monitoring” to “immediate intervention.”
Beyond the tape, we look for the physical markers that the spreadsheets often miss. We check for bilateral pitting edema—swelling in both feet—which tells us the body is failing to maintain protein levels. It’s a clinical reality that no amount of donated grain can fix if the underlying clinical malnutrition management isn’t strictly followed. We aren’t just looking for a number on a scale; we are looking for the physiological breakdown. The goal isn’t to check a box for a donor report; it’s to ensure the therapeutic feeding protocols are actually reaching the kid in the queue before their organs start to shut down.
The Gap Between Protocol and Delivery
A clinician can spend an hour measuring mid-upper arm circumference and documenting a perfect case of SAM, but that diagnosis is just a piece of paper if the RUTF isn’t sitting in the warehouse or the supply truck is stuck behind a washed-out bridge. You don’t treat malnutrition with a spreadsheet; you treat it with a functional supply chain.
Yusuf Lindqvist
The Reality of the Last Mile

We have covered the technicalities: the MUAC tapes, the edema checks, and the specific therapeutic foods required to stabilize a patient. But diagnosing malnutrition is only half the battle. You can have the most accurate clinical assessment in the world, but if the RUTF (Ready-to-Use Therapeutic Food) is sitting in a warehouse in a capital city because of a broken axle or a closed border, that diagnosis is nothing more than a death sentence on paper. The transition from clinical identification to actual treatment depends entirely on the integrity of the supply chain. If the medicine doesn’t reach the clinic, the statistics don’t matter.
At the end of the day, we need to stop getting lost in the high-level metrics of “program coverage” and start looking at the ground truth. Success isn’t found in a glossy annual report or a successful fundraising gala; it is found in the quiet, unglamorous reality of a delivered shipment. When we focus on the mechanics of getting the right nutrients to the right person at the right time, we move past sentiment and into actual impact. The goal isn’t to manage a crisis; it is to ensure the lorry arrives.





